

Coding · November 6, 2026
Dermatology Consultation CPT Code Guide: 99242-99245, Medicare Rules and What to Bill Instead
Original Medicare has not paid consultation codes 99242-99245 since January 1, 2010, so referred Medicare patients are billed with office or hospital E/M codes instead. This guide covers the 3-year new patient rule, leveling by MDM or time, same-day procedures, the 2027 Medicare change and how commercial plans differ.
This article is part of the dermatology billing blog, where we cover coding, denials and payer policy as they change.
More articles
- Basal Cell Carcinoma ICD-10 Codes (C44.x): How to Code BCC for Dermatology Billing
- Skin Cancer Screening CPT Code: How to Bill a Full Body Skin Exam With Z12.83 (2027 Guide)
- 2027 Medicare Physician Fee Schedule for Dermatology: What Changes on January 1, 2027
- Skin Tag Removal CPT Codes 11200 and 11201: How to Code and Count (2026)
- LCD vs NCD in Medical Billing: What Dermatology Practices Need to Know in 2026
- GZ Modifier: Complete Guide to Advance Beneficiary Notice Denials and Compliance
In this guide
- Dermatology consultation CPT code levels at a glance
- What counts as a consultation?
- How Medicare handles consultation codes
- What to bill Medicare instead, by setting
- Consult vs new patient visit in dermatology: the 3-year rule
- How do you choose the level by MDM or time?
- Consults and same-day dermatology procedures
- Commercial and Medicare Advantage plans
- Common consultation billing mistakes
- Get your consult claims checked
- Sources
- About the author
- Frequently Asked Questions

Quick answer: The dermatology consultation CPT code for an office consult is 99242, 99243, 99244 or 99245, leveled by medical decision making or total time (20, 30, 40 or 55 minutes). Original Medicare has not paid consultation codes since January 1, 2010. For Medicare patients, bill 99202-99205 or 99211-99215 in the office and 99221-99223 for hospital inpatients. Commercial and Medicare Advantage plans each set their own policy.
A referral letter on the chart tempts many front desks to code a consult. For an Original Medicare patient, that claim comes back unpaid and has to be recoded before any money moves.
The rules keep moving. CPT deleted 99241 on January 1, 2023. Blue Cross and Blue Shield of New Mexico stopped paying consult codes on November 18, 2024. On November 4, 2026, CMS finalized a payment cut for office visits billed with 0-day procedures, starting January 1, 2027.
This guide is for dermatology billers, coders and practice managers. It sits under our dermatology coding services hub and covers which code to send to each payer.
In this guide
- Dermatology consultation CPT code levels at a glance
- What counts as a consultation?
- How Medicare handles consultation codes
- What to bill Medicare instead, by setting
- Consult vs new patient visit in dermatology: the 3-year rule
- How do you choose the level by MDM or time?
- Consults and same-day dermatology procedures
- Commercial and Medicare Advantage plans
- Common consultation billing mistakes
- Get your consult claims checked
- Frequently asked questions
Dermatology consultation CPT code levels at a glance
Office consultation codes 99242, 99243, 99244 and 99245 match straightforward, low, moderate and high medical decision making (MDM). By time, they need 20, 30, 40 and 55 minutes, per the American Medical Association (AMA) 2023 E/M code and guideline changes.
The right two columns matter more for most dermatology practices. When a payer refuses consult codes, the same MDM level points you to the matching office visit code, using the code-to-MDM grid in the AMA E/M office revisions table.
Table 1. Office consult levels and the office visit codes at the same MDM level
| Consult code | MDM level | Minimum total time (CPT) | New patient code, same MDM | Established patient code, same MDM |
|---|---|---|---|---|
| 99242 | Straightforward | 20 minutes | 99202 | 99212 |
| 99243 | Low | 30 minutes | 99203 | 99213 |
| 99244 | Moderate | 40 minutes | 99204 | 99214 |
| 99245 | High | 55 minutes | 99205 | 99215 |
The time column belongs to the consult codes only. Office visit codes carry their own time thresholds, so recheck the time when you switch a time-based consult to an office code.
What counts as a consultation?
A consultation is a visit requested by another physician, qualified health care professional or appropriate source for an opinion on a specific problem, with a written report back to the requester. The AMA 2023 guidelines also let the consultant start testing or treatment at that visit or later.
These visits are not consultations under CPT, even when a payer still pays consult codes:
- Patient-initiated visits: a patient or family member who books a second opinion without a request from a clinician or other appropriate source gets an office visit code.
- Transfer of care: when the dermatologist takes over management of the whole condition, CPT routes the visit to new or established office codes.
- Follow-ups: later visits started by the consultant or the patient use established patient codes 99212-99215.
- Clinician-to-clinician advice without seeing the patient: these are interprofessional consults, 99446-99449, 99451 and 99452, covered in our teledermatology billing guide.
When a third-party payer mandates the consult, CPT adds modifier 32. CPT also allows 99242-99245 in the home or residence and the emergency department, not only the office.

How Medicare handles consultation codes
Original Medicare stopped recognizing all CPT consultation codes for services on or after January 1, 2010, under CMS Transmittal 1875, Change Request 6740. The May 2026 MLN006764 booklet still lists 99242-99245 and 99252-99255 as not recognized for Part B.
CMS gave the consult codes status indicator "I", meaning Medicare uses another code for the service. Per MLN Matters SE1010, a claim with a consult code is returned to the provider for recoding rather than denied.
Why an ABN does not help
An advance beneficiary notice (ABN) cannot shift the cost of a consult to a Medicare patient. SE1010 explains that the visit is still covered when medically necessary, so the patient owes only the deductible and coinsurance on the correct E/M code.
The only consultation codes Medicare does recognize are the telehealth consultation G-codes G0406-G0408 and G0425-G0427.
What to bill Medicare instead, by setting
For an Original Medicare patient, bill the E/M code for where the visit happened and how complex it was. That means 99202-99205 or 99211-99215 in the office, office codes for a patient in hospital observation, and 99221-99223 for a hospital inpatient.
Table 2. Medicare replacement codes for consult-type visits by setting
| Setting | Code family to bill | Notes | Source |
|---|---|---|---|
| Office, place of service (POS) 11 | 99202-99205 new or 99211-99215 established | New vs established follows the 3-year rule | MLN006764 |
| Hospital outpatient observation | Office or other outpatient codes | Only the treating practitioner bills observation care codes | Claims Processing Manual Ch. 12, 30.6.8 |
| Hospital inpatient | 99221-99223 initial care | A subsequent care code may be billed when the documented work fits it | MLN Matters SE1010 |
| Nursing facility | 99304-99306 initial care | Subsequent care codes when initial requirements are not met | MLN Matters SE1010 |

Hospital inpatient and observation
In the hospital, every physician who performs an initial evaluation may bill 99221-99223, according to Transmittal 1875. Only the admitting or attending physician adds the principal physician of record modifier, AI. SE1010 calls that modifier informational, so a dermatology consultant leaves it off.
For a patient in observation, the dermatologist bills new or established office or outpatient codes. Section 30.6.8 of the Medicare Claims Processing Manual, Chapter 12 reserves observation care codes for the treating practitioner.
The office workflow comes down to these steps:
- Confirm the payer is Original Medicare, not a Medicare Advantage plan.
- Search the practice record for any same-specialty professional service in the past 3 years.
- Select 99202-99205 when there is none, or 99211-99215 when there is.
- Level the visit by MDM or by full total time.
- Add modifier 25 only if a same-day procedure was performed and the E/M was separate work.
Consult vs new patient visit in dermatology: the 3-year rule
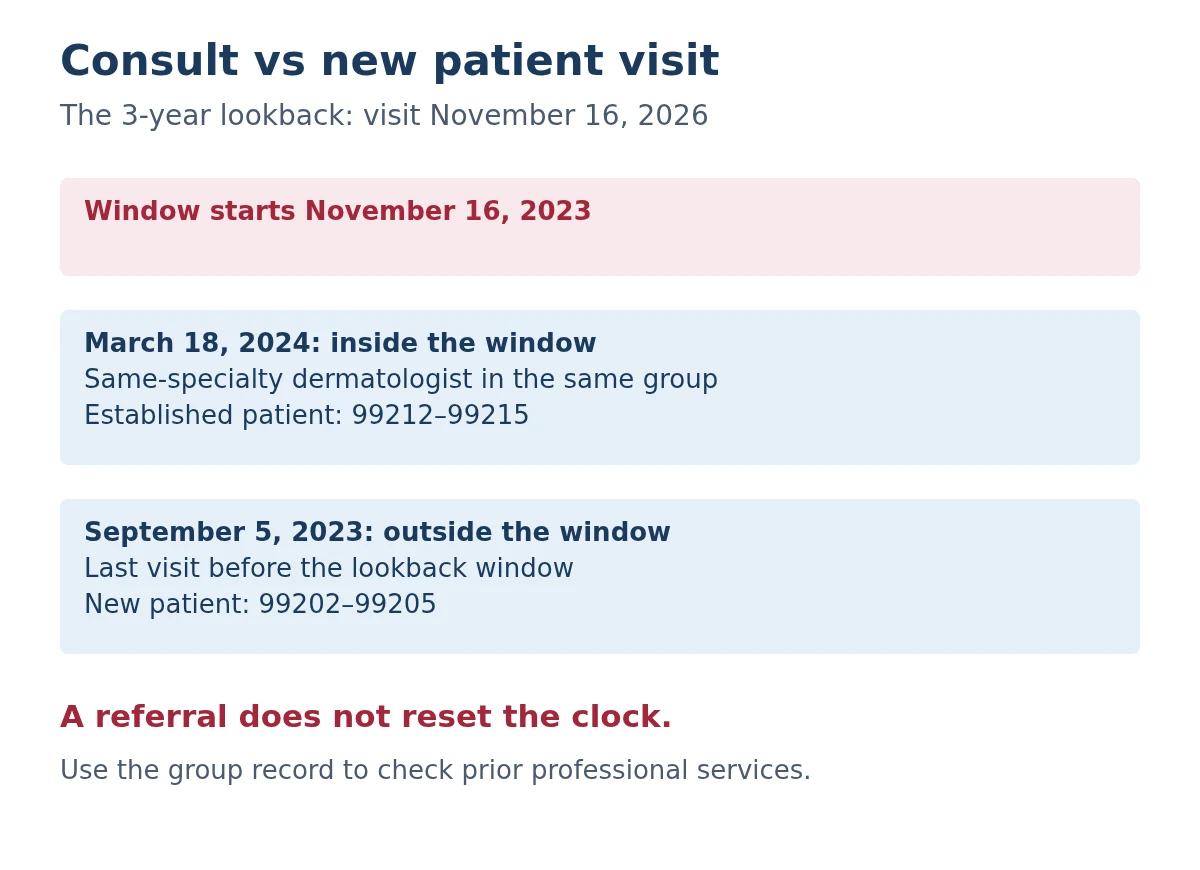
A Medicare patient is new when they have not received any professional service from the physician, or from a physician of the same specialty in the same group, within the previous 3 years. Chapter 12, section 30.6.7 states this rule, last revised May 7, 2026.
A referral does not reset the clock. SE1010 says a provider who saw the patient within 3 years cannot bill a new patient code, even for a pre-operative consult requested by a surgeon.
A test interpretation with no face-to-face service, such as a lab interpretation, does not make the patient established. A face-to-face service, such as a surgical procedure, does.
Worked example. A primary care physician refers an Original Medicare patient to a dermatology group for a changing lesion, and the visit is November 16, 2026. The 3-year lookback starts November 16, 2023.
- If another dermatologist in the group last saw the patient on March 18, 2024, that visit falls inside the window. Bill an established code, 99212-99215.
- If the last visit was September 5, 2023, it falls outside the window. Bill a new patient code, 99202-99205.
Our snowbird season billing post shows how the same lookback works when seasonal patients return.
How do you choose the level by MDM or time?
Since January 1, 2023, most E/M families are leveled by MDM or by total time on the date of the encounter. Chapter 12, section 30.6.1 keeps a medically appropriate history and exam as a requirement, but neither sets the level.
MDM is met when 2 of its 3 elements reach the level: problems addressed, data reviewed and analyzed, and risk of patient management. Our E/M glossary entry explains each element.
Medicare adds one rule for time. The full time must be met, and the CPT midpoint rule for timed services does not apply, according to MLN006764.
Prolonged time on a long consult
For a commercial plan that pays consults, CPT add-on 99417 goes with 99245 only when time selected the level. Under the AMA 2023 guidelines, the first unit starts at 70 minutes.
Medicare uses G2212 instead. MLN006764 shows 99205 plus one unit of G2212 at 89 to 103 minutes of total time.
Consults and same-day dermatology procedures
A consult or office visit and a procedure on the same day can both be paid when the E/M is significant and separately identifiable, with modifier 25 on the E/M. Chapter 12, section 30.6.6 adds that different diagnoses are not required.
The procedure is coded on its own line; see our skin biopsy coding guide and skin tag removal guide for 11200-11201. Our modifier 25 guide covers the documentation test.
Two Medicare details catch dermatology practices:
- Modifier 57 timing: Medicare pays an E/M with modifier 57 on the day of or day before a 90-day global procedure. It does not pay modifier 57 on those days for a 0-day or 10-day global procedure.
- G2211 in 2026: Medicare does not pay G2211 when the base E/M carries modifier 25, except with an annual wellness visit, vaccine administration or a Part B preventive service.
What changes on January 1, 2027
The calendar year 2027 Physician Fee Schedule final rule fact sheet, released November 4, 2026, cuts same-day pay for office E/M visits billed with a 0-day global procedure. When the same physician or practice bills both, Medicare pays the most expensive service at 100% and the other at 80%.
CMS dropped 10-day and 90-day globals from the final policy and replaced G2211 with modifier B1, which adds 16% to the E/M. Check each procedure's global indicator in the fee schedule before you forecast 2027 revenue, and read our 2026 Medicare fee schedule post for the current year.
Not sure your E/M and consult claims are coded right? Request a free claims audit.
Commercial and Medicare Advantage plans
Commercial and Medicare Advantage plans each decide whether to pay 99242-99245, so the answer comes from the plan's own payment policy. SE1010 limits the Medicare rule to fee-for-service and tells providers to contact the Medicare Advantage plan.
Table 3. Payer examples taken from each payer's own pages
| Payer and product | Consult codes paid? | Effective date | Source |
|---|---|---|---|
| Original Medicare Part B | No, 99242-99245 and 99252-99255 | January 1, 2010 | CMS MLN006764 |
| Blue Cross and Blue Shield of New Mexico, policy CPCP024 | No, 99242-99245 and 99252-99255 | November 18, 2024 | Blue Cross and Blue Shield of New Mexico notice |
| Independence Blue Cross Medicare Advantage preferred provider organization (PPO), policy MA00.049a | No, consult codes not eligible | June 6, 2022 version | Independence Blue Cross policy |
These rows are examples, not a list of every plan. Before you load consult codes into a fee schedule, check these points for each contract:
- Payment policy: find the plan's written evaluation and management or consultation policy and note its effective date.
- Product line: confirm whether commercial, exchange and Medicare Advantage products follow the same rule.
- Documentation: confirm the plan accepts a referral on file plus the written report as proof of the request.
- Review date: set a yearly reminder to recheck the policy, and recheck sooner when the plan posts a coding notice.
When Medicare is the secondary payer
Medicare will not accept a consult code as secondary either. SE1010 gives two options. You can bill the primary payer an E/M code and send Medicare that same code. Or you can bill the primary a consult code and send Medicare an appropriate E/M code; either way, report the primary's paid amount.

Common consultation billing mistakes
Most consult-related rework traces back to a handful of charge-entry habits:
- Sending 99242-99245 to Original Medicare: the claim returns for recoding. Build a payer edit that blocks consult codes for Medicare Part B.
- Coding every referral as new: a same-specialty partner's visit 2 years ago makes the patient established. Search the whole group record before choosing the code.
- Billing 99241: the code was deleted for 2023. Remove it from superbills and the charge master.
- Skipping the written report: a payer that pays consults expects the report to the requesting clinician. Store it with the visit note.
- Asking the patient to sign an ABN for a consult: Medicare does not allow it for this situation, and the patient owes only cost sharing on the E/M code.
- Leaving modifier 25 on by default: add it only when the note shows separate E/M work.
Get your consult claims checked
DermBillingUSA codes dermatology E/M visits by payer, so consult codes go only to plans that pay them and Medicare referrals go out with the right new or established code. If consult claims keep coming back for recoding, or you want modifier 25 use reviewed before the January 1, 2027 change, an audit is the place to start.
Not sure your E/M and consult claims are coded right?
Sources
- Evaluation and Management Services, MLN006764 (May 2026), Centers for Medicare & Medicaid Services
- Medicare Claims Processing Manual, Chapter 12, Physicians/Nonphysician Practitioners (Rev. 13753, May 7, 2026), Centers for Medicare & Medicaid Services
- Transmittal 1875, Change Request 6740: Revisions to Consultation Services Payment Policy (December 14, 2009), Centers for Medicare & Medicaid Services
- MLN Matters SE1010: Questions and Answers on Reporting Physician Consultation Services, Centers for Medicare & Medicaid Services (HHS guidance portal copy)
- Calendar Year 2027 Medicare Physician Fee Schedule Final Rule fact sheet (November 4, 2026), Centers for Medicare & Medicaid Services
- CPT Evaluation and Management (E/M) Code and Guideline Changes, effective January 1, 2023, American Medical Association
- 2021 E/M Updates: EHR Workflow and Operational Considerations, with CPT Table 2 Level of MDM, American Medical Association
- Revised Effective Date: Reimbursement Change for Consultation Services, Now Nov. 18, 2024, Blue Cross and Blue Shield of New Mexico
- Consultation Services, MA PPO Claim Payment Policy MA00.049a, Independence Blue Cross
About the author
Touseef Riaz is Founder & Chief Executive Officer of DermBillingUSA, the dermatology-only billing, coding and revenue cycle brand of Practice Revenue Management, Inc.
Frequently Asked Questions
The office codes are 99242-99245, leveled by MDM or total time. Original Medicare does not accept them, so Medicare referrals are billed with 99202-99205 or 99211-99215 in the office.
No. Original Medicare has not recognized consultation codes since January 1, 2010, and a claim with one is returned for recoding. Medicare does recognize the telehealth consultation G-codes G0406-G0408 and G0425-G0427.
Bill the E/M code for the setting, not a consult code. In the office, use a new patient code 99202-99205 only when nobody in your group of the same specialty gave the patient a professional service in the previous 3 years; otherwise use 99211-99215.
No. CPT deleted 99241 on January 1, 2023, and 99242 is now the lowest office consultation level.
Yes, when the E/M is significant and separately identifiable, with modifier 25 on the E/M. From January 1, 2027, Medicare pays the less expensive service at 80% when the same physician or practice bills an office E/M with a 0-day global procedure.
Not always. Each plan sets its own written policy, CMS tells providers to contact the Medicare Advantage plan, and Independence Blue Cross's Medicare Advantage PPO policy, for example, does not pay consult codes.